

Spondylodiscitis Treatment: Diagnosis, Medication & Surgery
Learn how spondylodiscitis is diagnosed, how long antibiotics or TB drugs take, and when surgery is needed. By a Bangalore spine surgeon.
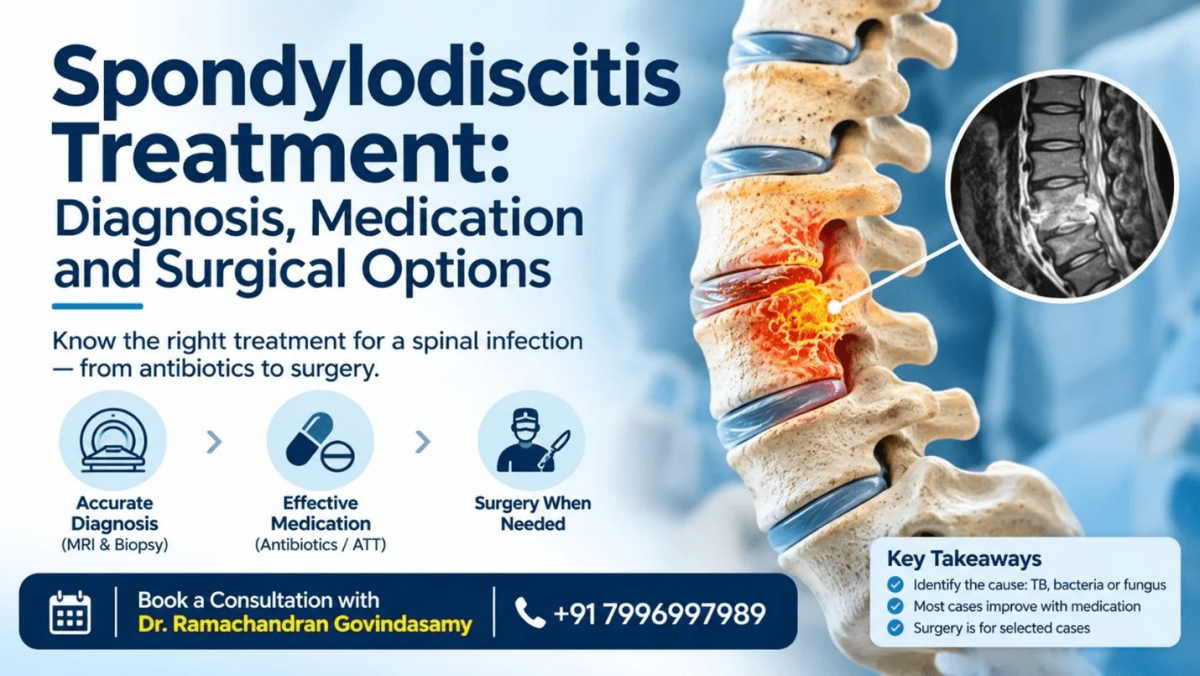
Quick answer: Spondylodiscitis is an infection of a spinal disc and the vertebrae next to it. It is diagnosed with MRI, blood tests (ESR, CRP) and, ideally, a CT-guided biopsy that identifies the exact organism. Most people are treated with medicine alone: about 6 weeks of antibiotics for a bacterial infection, or many months of anti-tubercular therapy (ATT) for spinal TB. Surgery is kept for an unstable spine, nerve or spinal cord compression, progressive deformity, or a large abscess.
Key facts at a glance
- TB and bacterial infections look alike on scans but need completely different drugs. That is why identifying the organism matters.
- A large French randomised trial found 6 weeks of antibiotics worked as well as 12 weeks for bacterial vertebral infection, with about 91% of patients cured at one year in both groups.
- Most patients do not need an operation.
If you have back pain along with fever, night sweats or weight loss, don't wait for it to settle on its own. At Spine DRx in Bangalore, spinal infections are diagnosed and treated by Dr. Ramachandran Govindasamy.
Book a consultation with Dr. Ramachandran → or call +91 7996997989
What is spondylodiscitis?
Spondylodiscitis is an infection that starts in the soft cushion between two vertebrae (the disc) and spreads into the bone above and below it. Doctors use several names for it: discitis, vertebral osteomyelitis, spinal infection, and, when tuberculosis is the cause, Pott's spine.
Germs usually reach the spine through the bloodstream, from the lungs, urinary tract, skin or a tooth, or sometimes during a spine procedure. Once there, the infection forms pus, weakens the bone and can press on the nerves or spinal cord.
There are three broad causes, and the treatment plan depends entirely on which one you have:
- Tuberculous (TB) spondylodiscitis: the most common cause in India. It builds up slowly over months and can affect people who are otherwise healthy.
- Pyogenic (bacterial) spondylodiscitis: often comes on over days. It is more likely in older adults, people with uncontrolled diabetes, kidney failure on dialysis, liver disease, weak immunity, or recent spine surgery or injections.
- Fungal: uncommon, mostly seen when immunity is very low.
You can read the clinic's overview on our page for spondylodiscitis treatment in Bangalore. This article goes deeper into how the decisions get made.
Symptoms that should make you see a doctor
Spinal infection is easy to miss because the first symptom, back or neck pain, is something almost everyone has. What gives it away is the company the pain keeps.
Bacterial infection: sudden severe back pain, high fever, and feeling suddenly unwell within days.
Spinal TB:
- Back or neck pain building over weeks or months, often worse at night
- Evening fever and night sweats
- Loss of appetite and weight loss
- Later: a visible hump (kyphosis), or numbness or weakness in the legs
Go to an emergency department the same day if you have: new weakness in the legs, numbness around the groin or buttocks, trouble passing urine or stool, or severe back pain with high fever. These can mean the spinal cord or nerves are being compressed, and time matters.
For a broader checklist, see our guide on when you should see a spine surgeon. If your pain has been there for a while and you're unsure about the cause, what causes lower back pain is a useful starting point.
Back pain that comes with fever, night sweats or weight loss deserves a proper spine evaluation, not another painkiller. Request an appointment → WhatsApp us
How spondylodiscitis is diagnosed
No single test settles it. Diagnosis is built from the story you tell, the examination, blood work, imaging and, most importantly, tissue.
| Step | What it tells us |
| History and neurological examination | Duration of symptoms, risk factors, and whether nerves or the cord are affected |
| Blood tests (CBC, ESR, CRP) | Whether there is infection or inflammation, and a baseline to track treatment response |
| MRI of the spine | The most useful scan: shows disc and bone involvement, abscesses, and pressure on the cord or nerves |
| X-ray and CT scan | How much bone is damaged and whether the spine is stable |
| CT-guided biopsy (with blood or urine cultures where needed) | Identifies the cause (TB, bacteria or fungus), the drugs that will work, and where the infection came from |
Why the biopsy matters
TB and bacterial infections can look almost identical on an MRI. Treating on a guess can mean months of the wrong medicine and, in TB, a risk of drug resistance. Antibiotics taken before a biopsy can also make it harder to grow the organism afterwards.
That is why, in Dr. Ramachandran's practice, a suspected spinal infection is sampled with a CT-guided biopsy first, and treatment is based on the result. The one exception is a critically ill patient, such as someone with sepsis or rapidly worsening nerve function. Samples are taken and treatment starts straight away.
Already have an MRI? Bring the films, not just the report. Get your MRI reviewed →
Medication: the foundation of treatment
For most patients, medicine is the treatment. Surgery is the exception.
Bacterial (pyogenic) spondylodiscitis: antibiotics
Antibiotics are chosen to match the organism and to reach bone effectively. Current guidance, including the 2015 Infectious Diseases Society of America guideline, points to about 6 weeks. A randomised trial of 359 patients in France found 6 weeks non-inferior to 12, with about 91% cured at one year in each group. Treatment may start with intravenous antibiotics and continue as tablets. It can run longer if there is an abscess, a resistant organism or extensive bone destruction.
Spinal TB: anti-tubercular therapy (ATT)
Spinal TB is treated with a combination of anti-tubercular drugs for many months. Published recommendations range from about 6 to 18 months, and the course is adjusted to your response on examination, blood tests and follow-up MRI. For a stable spine, Dr. Ramachandran typically plans 12 to 18 months. The most common reason spinal TB fails is stopping early because the pain has gone, which is also how drug-resistant TB develops. Take every dose and keep every follow-up.
Comparing the options
| Bacterial (pyogenic) | Tuberculous (spinal TB) | |
| Typical onset | Days | Weeks to months |
| Main treatment | Targeted antibiotics | Anti-tubercular therapy (ATT) |
| Typical duration | About 6 weeks (longer if abscess or resistant organism) | Many months; commonly 12 to 18 months for a stable spine |
| How the drug is chosen | Biopsy or blood culture and sensitivity | Biopsy with TB testing and drug sensitivity |
| Surgery needed? | Only in select cases | Only if unstable, deformed or nerves are compressed |
When is surgery needed, and what does it involve?
Most people with spondylodiscitis recover without an operation. Surgery becomes the right choice when medicine alone cannot protect the spine or the nerves. The usual reasons are:
- Nerve or spinal cord compression causing weakness, numbness or loss of bladder or bowel control
- Spinal instability, where infection has destroyed enough bone that the spine can collapse or shift
- Progressive deformity, especially a worsening kyphosis (forward hump)
- A large abscess pressing on neural structures
- No improvement on the right medicine, or an inconclusive biopsy
The operation takes pressure off the nerves, clears infected tissue and stabilises the spine with rods and screws, often through a single-stage approach from the back. Whenever the spine allows it, the least invasive method that does the job safely is used. Dr. Ramachandran trained in minimally invasive spine surgery at the AO Spine Center in Erfurt, Germany, and uses navigation and robotic guidance where they suit the case. Antibiotics or ATT continue after surgery.
Read more about spine surgery in Bangalore, minimally invasive spinal fusion, MIS tubular decompression and robotic spine surgery. If infection has left a spinal curve or pressed on the cord, see kyphosis treatment and cervical myelopathy. Our guide on spine surgery versus non-surgical treatment explains how that decision is made.
Told you need surgery for a spine infection? Get a second opinion before you decide. Dr. Ramachandran will review your MRI and tell you plainly whether surgery is needed, and if it isn't, what the alternative is. Book a second-opinion consultation →
Recovery, follow-up and preventing a relapse
What improvement looks like. Fever and severe pain usually ease first, and CRP and ESR fall over the following weeks. MRI lags behind how you feel, so your doctor reads the whole picture, not just the latest scan.
Follow-up. Expect regular blood tests and, when needed, repeat imaging during and after the course. Many relapses happen because follow-up stopped too early.
Activity and rehabilitation. Rest and sometimes a brace protect the spine early on. Once it is stable, physiotherapy rebuilds strength and movement.
Lowering the chance of it coming back:
- Finish the full medicine course, even when you feel well
- Keep diabetes tightly controlled
- Treat infections elsewhere in the body promptly
- Tell any doctor planning a spine procedure about your history
Pain that persists or returns should be checked, not assumed to be "just scarring." See our page on neck and back pain treatment.
Why choose Dr. Ramachandran for spine infection care in Bangalore
Spinal infection is a condition where the diagnosis decides the outcome, so experience counts.
Dr. Ramachandran Govindasamy is a consultant Spine & Deformity Surgeon at the Aster International Institute of Neurosciences & Spine Care, Aster Whitefield Hospital, Bangalore. He has more than 14 years of dedicated spine practice and consults at the Spine DRx clinics in Whitefield and Kasavanahalli.
- Qualifications: MBBS (Madras Medical College), MS Orthopaedics (Sawai Man Singh Medical College, Jaipur) and DNB Orthopaedics
- Training: Spine Surgery at Manipal Hospitals, Bangalore; UCSF (Indo American Spine Alliance); minimally invasive spine surgery at the AO Spine Center, Erfurt, Germany
- Experience with spinal infection: presented on pyogenic spondylodiscitis, covering challenges in diagnosis and a treatment algorithm, at national spine conferences in 2019 (ASSI ICS, Mangalore and NSSA Spine, Kochi)
His approach is biopsy-first and evidence-based: identify the organism, match the treatment to it, and operate only when there's a clear reason to. Read his full profile or see real cases from our clinic.
Take the next step
Spinal infection is very treatable when it is caught early and treated for the right cause. The harder part is usually getting the right diagnosis first.
If you or a family member has persistent back pain with fever, night sweats or weight loss, or has been told there is an infection in the spine and wants a clear plan, Dr. Ramachandran can help.

Dr. Ramachandran Govindasamy, an experienced orthopedic spine surgeon specializing in the diagnosis and treatment of spinal disorders.










Comments (0)